College of Life Sciences
From Challenge to Change: How Listening Created a More Inclusive Clinical Learning Environment
Salma Jamal Habboub, Medical Student, Leicester Medical School and Sarah Staunton, Matron, Leicester Partnership Trust
Salma’s Voice:
On my first day of my placement with the Leicestershire Partnership NHS Trust (LPT), just finishing the ward round, I was standing in the corridor with an Advanced Care Practitioner, planning how to approach the day, when a staff member asked me to roll up my sleeves in line with the bare below the elbows (BBE) policy.
As I wasn’t undertaking clinical activity at the time (I’ve since realised that there is some ambiguity in the different policies across different Trusts as to exactly what this means! And that it isn’t always ‘direct patient care activity’ as defined in national guidance), I explained that whilst I am bare below the elbows – or I use disposable oversleeves – when undertaking patient care, I was unable to roll up my sleeves outside of that setting for religious and personal reasons. I was told that this was the policy and that the issue would be escalated.
Shortly after, the ward matron, Sarah, came to speak with me in the doctors’ office. She asked why I couldn’t roll up my sleeves, and I explained my reasons as I had previously. She told me that it was a policy requirement, and that if I didn’t comply, I wouldn’t be able to take part in clinical activities and would have to remain in the doctors’ office instead.
I was upset by this given the potential impact on my learning, and explained that I had experienced this repeatedly elsewhere, and that most of the time, people were quick to correct me and escalate the issue without taking the time to listen or understand my perspective. Sarah did listen however, and expressed a desire to support me in finding a way forward.
Though it is commonly used to refer to the headscarf, for me as a Muslim woman, hijab is a more holistic concept - it includes how I dress, how I speak, and how I carry myself. Covering my arms is part of that commitment. It is not simply a preference; it is a deeply held value and a part of my religious belief. As a healthcare professional in training, infection control and prevention is similarly a deeply held value, so I would never do anything to compromise this.
I left that day feeling disheartened and excluded. I felt I had struck the correct balance of BBE/using disposable oversleeves when undertaking direct patient care activity, whilst continuing to cover my arms in other settings, and this was being accepted in some Trusts, but not others. I was anxious day to day as to whether I might be asked to uncover a part of my body I had consciously chosen to cover. I was questioning whether I had to forgo my religious beliefs to be able to practise medicine.
Following this incident, I reached out to my personal tutor, who is part of the MedRACE team, seeking support and advice. While we worked to address the situation from within the medical school, the matter was also being escalated by Sarah to the Infection Prevention and Control (IPC) team.
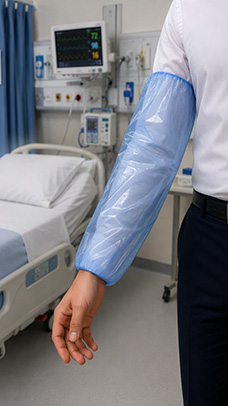 The speed of this response and the support from Sarah and other LPT colleagues was truly heartwarming. Per their already inclusive Hand Hygiene policy, they arranged to make disposable oversleeves available, and though initial advice was a ¾ length sleeve beneath disposable oversleeves, Sarah explored this further with the NHS England Lead for IPC, who advised that I could wear a full-length sleeve beneath the disposable oversleeves.
This was accompanied by clear guidance (now also in the updated LPT Hand Hygiene Policy) on exactly how these oversleeves were to be used whilst ensuring strict infection prevention and control.
As I’m writing this, I’m thinking of all of those who were uncomfortable rolling up their sleeves but were afraid to speak up - real change rarely starts in formal meetings, it often begins in uncomfortable, ordinary situations; inside corridors, wards, and conversations that may seem small at the time but later shape decisions that affect many others. Despite multiple similar incidents in other Trusts, I was never asked about my perspective, never felt supported in the way that I was this time.
I am forever grateful to Sarah and the LPT and MedRACE colleagues who have worked towards ensuring a more inclusive and welcoming learning environment – not just for me, but for others who might be in a similar position now and in the future.
Sarah’s Voice:
I am one of the Leicestershire Partnership Trust (LPT) Matrons and was contacted by one of my Ward Sisters, for some advice regarding medical student Salma, who was on placement on Beechwood ward at the Evington Centre. The Ward Sister informed me that due to religious reasons, Salma had refused a request to be bare below the elbows whilst working clinically on the ward. Whilst LPT has clear Infection Prevention and Control Policies in place regarding clinical staff being bare below the elbows, it was important for me to speak with Salma directly to understand the situation and explain the trust policy.
On meeting Salma on the ward, I informed her of the LPT policy and explained that if Salma was to work clinically on the ward, she would need to be bare below the elbows. Salma explained her reasons for not being able to be bare below the elbows but did state that she could wear oversleeves in the clinical area.
Based on my knowledge of the trust’s IPC policy, I advised Salma that I would need to review the policy for specific guidelines regarding the wearing of oversleeves and that I would need to take advice from the IPC Lead Nurse. Salma went on to explain that she experienced challenges during other placements regarding her request for being bare below the elbows and that the situation she found herself in each time was very distressing. I was very conscious that I did not want to add to Salma’s distress and wanted to find a workable solution for her whilst also following the trust’s IPC policy.
After meeting with Salma, I immediately reviewed the LPT IPC policy regarding the guidance for use of oversleeves and I also contacted the LPT Lead Nurse for IPC. The advice I initially received was that although disposable oversleeves can be provided, Salma would need to wear a ¾ length (or less) sleeve underneath the disposable oversleeve and that her own ¾ sleeve should not be loose fitting. I explained to the IPC lead that for religious reasons Salma would not be able to wear a ¾ length sleeve underneath the disposable oversleeves, so the LPT Head of IPC escalated this to the NHS England Lead for IPC for further advice.
Following discussion with the NHS England IPC Lead, the advice given was that Salma was able to wear her own full-length sleeve underneath the disposable oversleeves, but that the oversleeves must be changed after every care/patient episode (single patient use) and must not prevent hand hygiene. As such, the oversleeves must be removed after each episode of care and Salma would then need to roll her own full-length sleeve up to complete the necessary hand and wrist washing.
I also instructed the ward to order some disposable oversleeves and liaised with the LPT Head of Education and Training Development. The Head of Education and Training promptly developed a Process chart to support students in accessing oversleeves.
I was very happy that I was able to help Salma and other potential staff working across LPT that may encounter problems with managing their religious beliefs whilst following LPT policy. It was also important for me to ensure that LPT policy supports the needs of staff in relation to their religious beliefs and whilst the policy did cover use of oversleeves, the specifics around how staff should maintain hand hygiene and what length of sleeve could be worn underneath was not clear. Following this incident and escalation, I am now confident that there is clear guidance in place.
